


Medical Terminology Daily - Est. 2012

Medical Terminology Daily (MTD) is a blog sponsored by Clinical Anatomy Associates, Inc. as a service to the medical community. We post anatomical, medical or surgical terms, their meaning and usage, as well as biographical notes on anatomists, surgeons, and researchers through the ages. Be warned that some of the images used depict human anatomical specimens.

You are welcome to submit questions and suggestions using our "Contact Us" form. The information on this blog follows the terms on our "Privacy and Security Statement" and cannot be construed as medical guidance or instructions for treatment.


We have 510 guests online


A Moment in History

William S. Halsted, MD

William S. Halsted, MD
(1852 – 1922)

American anatomist, teacher, and surgeon, William Stewart Halsted was born in New York City, USA to a wealthy family of English origin. His father was involved in charitable work and Governor and trustee to a city hospital. Not a brilliant student initially, Halsted took an undergraduate in Liberal Arts in Yale, CT., after which he entered the Medical College of Physicians at the Columbia College, where he excelled.

As a second-year medical student Halsted applied and obtained a position in surgery at a local hospital. In here he learned about Lister’s antiseptic technique and became an adamant proponent of it to reduce infection. In 1877 Halsted obtained his MD. After a short time as House Physician at the New York Hospital, Halsted traveled to Europe to further his education studying for two years at the Universities of Vienna, Leipzig, and W?rzburg.

Besides being at the forefront of surgical and antiseptic techniques (introducing the use of rubber gloves in surgery), Halsted was extremely concerned with the way medical students were taught in the US. He pioneered bedside clinical round discussions with the medical students after two years of basic sciences studies. Halsted developed the idea of a patient chart; he also developed the residency program for medical students in use today.

Halsted is probably the most influential researcher and surgeon at the turn of the century. He dedicated time to the study of intestinal anastomoses and the use of silk as a suture material. His experimental work in 1887 proved that the inclusion of the submucosa layer in an anastomosis was mandatory, as well that a single layered anastomosis was enough to attain closure. Perhaps Halsted’s most important contribution was the application and use of the scientific method to surgical questions. Halsted’s principles, also known as  "Halsted's Rules of Surgery", set the standards used today in surgical suturing and surgical stapling.

He also pioneered the development and surgical techniques for radical mastectomy as a treatment for breast cancer.

As a side effect of this studied in anesthesia and the use of cocaine for anesthesia, Halsted became addicted to this substance, a problem that followed him through the years. Without impairing his capacity as a researcher and a surgeon, Halsted eventually recovered. He died in Baltimore in 1922 as a complication to surgery.

Sources:
1. Dubay, A. D., & Franz, G. M. (2003). Acute Wound Healing: The Biology of Acute Wound Failure. Surg Clin NA, 83, 463-481.
2. Halsted, W. S. (1887). Circular Suture of the Intestine - An Experimental Study. Am J Med Sci, 436-461.
3. “William Stewart Halsted: his life and contributions to surgery” Osborne, P. Lancet Oncol 2007; 8: 256–65
4. “William Stewart Halsted: Surgical pioneer” Burress, P Endoc Today (2010), 8: (2) 22
5. “William Stewart Halsted (1852–1922) Neurological stamp” Haas, LF J Neurol Neurosurg Psych 2000;69:641
Original image courtesy of "Images from the History of Medicine" at  www.nih.gov


 "Clinical Anatomy Associates, Inc., and the contributors of "Medical Terminology Daily" wish to thank all individuals who donate their bodies and tissues for the advancement of education and research”.

Click here for more information


bookplateink.com


Tracheal bronchus (pig bronchus)

After writing an article on the tracheal bronchus, I was asked to describe the anatomy of the pig (Sus scrofa domesticus) lung and a comparison with the human lung. The function and general structure of the pig lung is similar to the human. Anatomy-wise... there are several differences.

It is important to understand that directional terminology used to describe the anatomy of the pig is different than that used for the human. We use the anatomical position for humans, but as the pig is a quadruped, there is no such position for the pig, and veterinary terminology is used.. For further information on this topic, click here.

Following are two images. The first one is an anterior view of the human lungs and their tracheobronchial tree. The second image shows a ventral view of the pig tracheobronchial tree and both lungs.
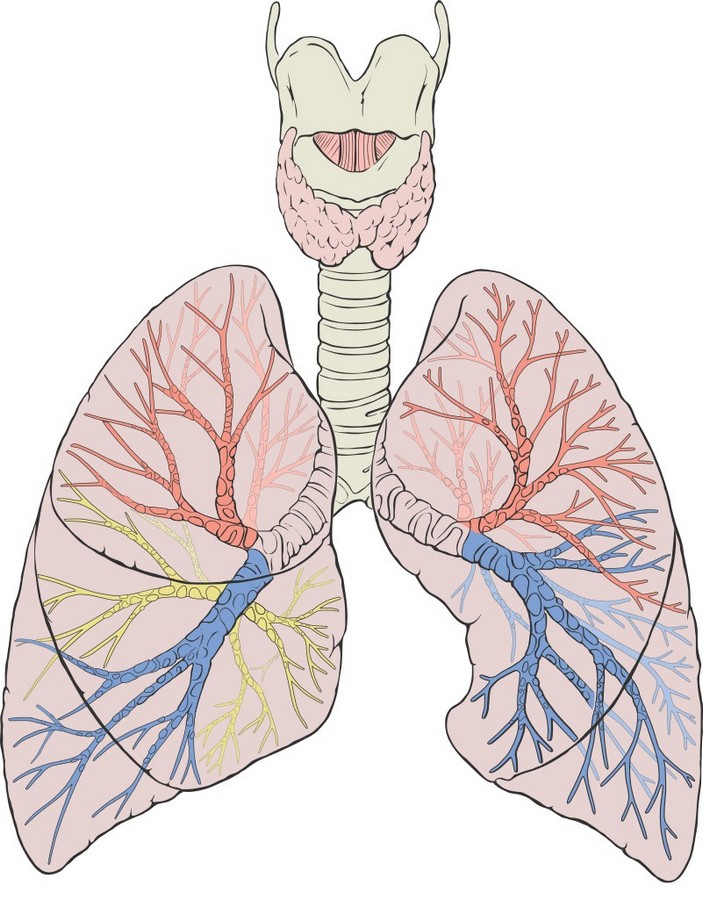
Anterior view of the human lungs and tracheobronchial treeAnterior view of the human lungs and tracheobronchial tree
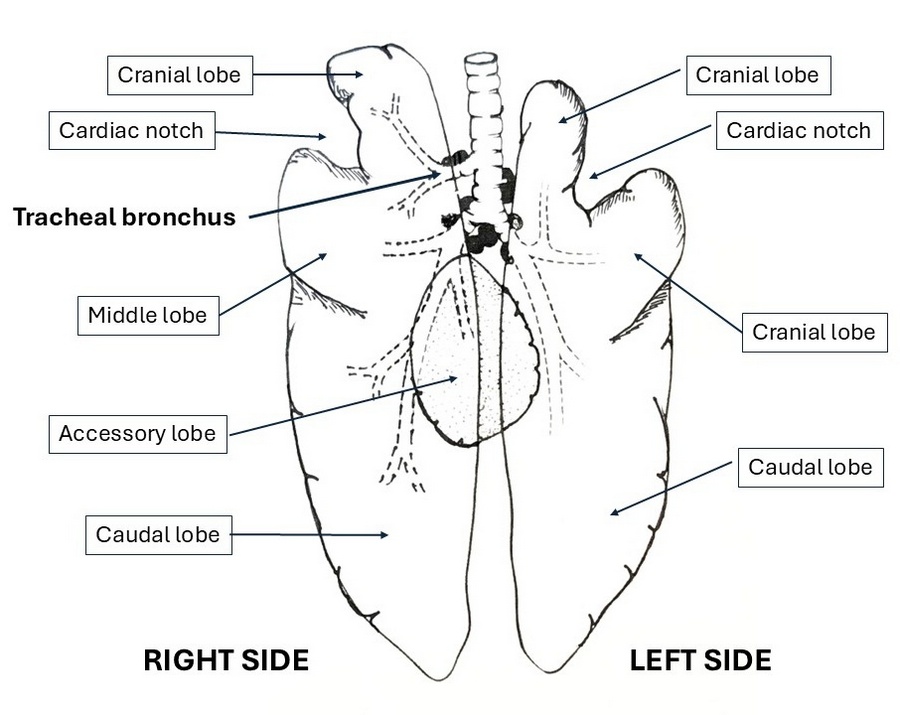
Pig lungs, ventral viewVentral view of the pig lungs and tracheobronchial tree

The first difference with the human lung is that there are two cardiac notches, right and left (the left cardiac notch is larger) whereas the human has only one, on the left lung.

The structure of the tracheobronchial tree in both species is similar, with incomplete cartilaginous rings and a posterior (dorsal) membrane that closes both the trachea and bronchi. Similarly, as the bronchial tree is more distal, the cartilaginous rings break up.

The trachea in the human ranges between 10 to 12 centimeters, while in the pig the trachea is longer, between 25 to 30 centimeters. Both bifurcate at the carina into a right and left main stem bronchus. In both species there is a large number of lymphatic nodes at the tracheal bifurcation (carinal nodes) which drain the lungs.

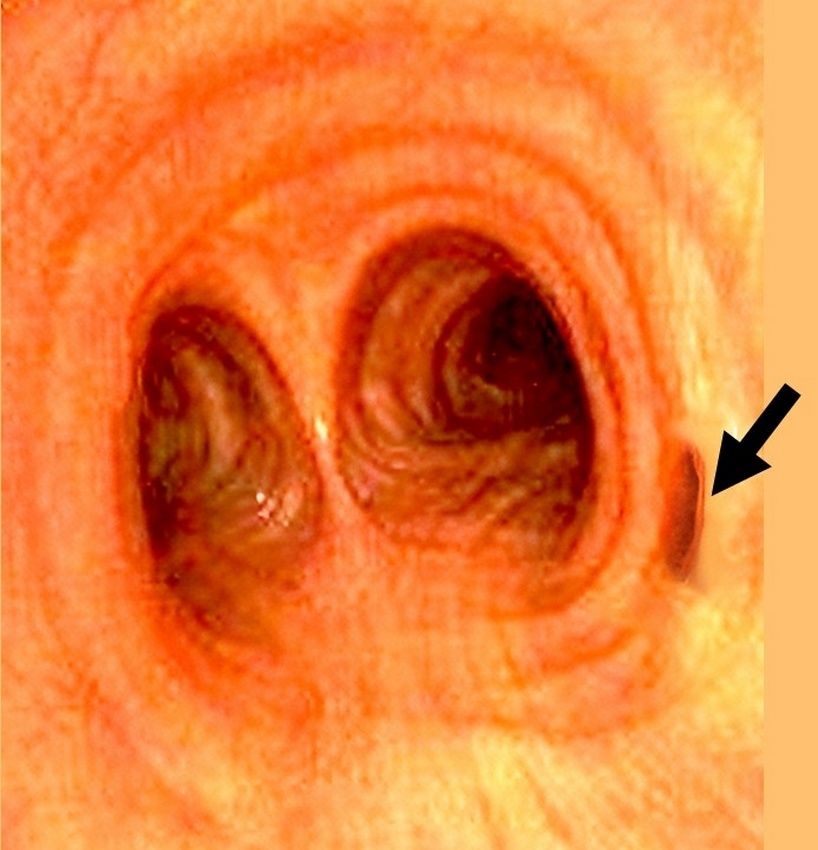
In the pig, the bronchus for the right cranial lobe arises directly from the trachea, and is known as the "tracheal bronchus". This does not normally happen in the human, and when it does it is considered an anatomical variation called a "pig bronchus", "bronchus suis", or "tracheal bronchus", and it can cause serious problems during intubation in surgery.

In the human, there are normally three lobes on the right side (upper, middle, and lower), and two on the left side (upper and lower). Each lobe has its separate lobar bronchus.

The right lung in the pig has 4 lobes: Cranial, middle, caudal, and an accessory lobe that is ventral and is located in the midline. Each lobe has its own separate lobar bronchus.

The left lung in the pig has two lobes: Cranial and caudal. The left cardiac notch splits the cranial lobe in two segments, but since these segments arise from a common bronchus, they are considered one lobe.

Sources:
1. "Essentials of Pig Anatomy" Sack, W.O.; Horowitz, A. 1982 Veterninary Textbooks, Ithaca, New York..
2. “Bronchial tree, lobular division and blood vessels of the pig lung” Nakakuki, S. J Vet Med Sci. 1994 Aug;56(4):685-9. 
3. “Bronchial anatomy and single-lung ventilation in the pig” Muton, WG. Can J Anesth 1999 46:7 p701-703

- Human tracheal bronchus endoscopic image modified from the original. Public domain.
- Anterior view of the human lungs and tracheobronchial tree image by . Patrick J. Lynch, medical illustrator, CC BY 2.5 <https://creativecommons.org/licenses/by/2.5>, via Wikimedia Commons.
- Ventral view of the Ventral view of the pig lungs and tracheobronchial tree image by Dr. Miranda, modified from the original. Public domain.