


Medical Terminology Daily - Est. 2012

Medical Terminology Daily (MTD) is a blog sponsored by Clinical Anatomy Associates, Inc. as a service to the medical community. We post anatomical, medical or surgical terms, their meaning and usage, as well as biographical notes on anatomists, surgeons, and researchers through the ages. Be warned that some of the images used depict human anatomical specimens.

You are welcome to submit questions and suggestions using our "Contact Us" form. The information on this blog follows the terms on our "Privacy and Security Statement" and cannot be construed as medical guidance or instructions for treatment.


We have 771 guests online


A Moment in History

William S. Halsted, MD

William S. Halsted, MD
(1852 – 1922)

American anatomist, teacher, and surgeon, William Stewart Halsted was born in New York City, USA to a wealthy family of English origin. His father was involved in charitable work and Governor and trustee to a city hospital. Not a brilliant student initially, Halsted took an undergraduate in Liberal Arts in Yale, CT., after which he entered the Medical College of Physicians at the Columbia College, where he excelled.

As a second-year medical student Halsted applied and obtained a position in surgery at a local hospital. In here he learned about Lister’s antiseptic technique and became an adamant proponent of it to reduce infection. In 1877 Halsted obtained his MD. After a short time as House Physician at the New York Hospital, Halsted traveled to Europe to further his education studying for two years at the Universities of Vienna, Leipzig, and W?rzburg.

Besides being at the forefront of surgical and antiseptic techniques (introducing the use of rubber gloves in surgery), Halsted was extremely concerned with the way medical students were taught in the US. He pioneered bedside clinical round discussions with the medical students after two years of basic sciences studies. Halsted developed the idea of a patient chart; he also developed the residency program for medical students in use today.

Halsted is probably the most influential researcher and surgeon at the turn of the century. He dedicated time to the study of intestinal anastomoses and the use of silk as a suture material. His experimental work in 1887 proved that the inclusion of the submucosa layer in an anastomosis was mandatory, as well that a single layered anastomosis was enough to attain closure. Perhaps Halsted’s most important contribution was the application and use of the scientific method to surgical questions. Halsted’s principles, also known as  "Halsted's Rules of Surgery", set the standards used today in surgical suturing and surgical stapling.

He also pioneered the development and surgical techniques for radical mastectomy as a treatment for breast cancer.

As a side effect of this studied in anesthesia and the use of cocaine for anesthesia, Halsted became addicted to this substance, a problem that followed him through the years. Without impairing his capacity as a researcher and a surgeon, Halsted eventually recovered. He died in Baltimore in 1922 as a complication to surgery.

Sources:
1. Dubay, A. D., & Franz, G. M. (2003). Acute Wound Healing: The Biology of Acute Wound Failure. Surg Clin NA, 83, 463-481.
2. Halsted, W. S. (1887). Circular Suture of the Intestine - An Experimental Study. Am J Med Sci, 436-461.
3. “William Stewart Halsted: his life and contributions to surgery” Osborne, P. Lancet Oncol 2007; 8: 256–65
4. “William Stewart Halsted: Surgical pioneer” Burress, P Endoc Today (2010), 8: (2) 22
5. “William Stewart Halsted (1852–1922) Neurological stamp” Haas, LF J Neurol Neurosurg Psych 2000;69:641
Original image courtesy of "Images from the History of Medicine" at  www.nih.gov


 "Clinical Anatomy Associates, Inc., and the contributors of "Medical Terminology Daily" wish to thank all individuals who donate their bodies and tissues for the advancement of education and research”.

Click here for more information


bookplateink.com


Esophageal hiatus hernia in situ.The arrow points to stomach and greater omentum herniating into the thorax
Esophageal hiatus hernia in situ.
The arrow points to stomach and greater
omentum herniating into the thorax

UPDATED: An esophageal hiatus hernia (also known as a hiatal hernia) is caused by a dilation of the esophageal hiatus and its component structures, the phrenoesophageal membranes (ligaments).

Since the intraabdominal pressure is higher than the intrathoracic pressure, abdominal contents -usually stomach and greater omentum- can herniate through the dilated esophageal hiatus into the mediastinum, the central region of the thoracic cavity. This presents as a hernia sac whose walls are formed by endothoracic fascia, phrenoesophageal membranes and parietal peritoneum. 

There are two main types of esophageal hiatus hernias. Type I is known as a "sliding hiatal hernia" and is characterized by a complete ascension of the esophagogastric junction and abdominal esophagus into the thoracic hernia sac. This is usually accompanied by a typical "hourglass image" in a radiographic assessment, and also presents with gastroesophageal reflux disease (GERD). Type I esophageal hiatus hernias are more common.

Esophageal hiatus hernia, reduced. The dotted line shows the edge of the enlarged esophageal hiatus
Esophageal hiatus hernia, reduced.
The dotted line shows the edge of
the enlarged esophageal hiatus

Type II esophageal hiatus hernia is known as a "paraesophageal hernia" and represent about 5 - 15% of esophageal hiatus hernias. In this case, the esophagogastric junction maintains its anatomical position inferior to the respiratory diaphragm, but the fundus and body of the stomach, along with some greater omentum herniate alongside the esophagus into the mediastinal region of the thoracic cavity. Although there can be GERD, this type of hernia usually presents with little symptomatology, and when it does, symptoms are related to ischemia or partial to complete obstruction. There are variations of type II hernia, which are classified as Type III and IV. Type IV, although rare, will include other viscera in the hernia sac, including colon, spleen, or even small intestine.

The accompanying images above depict a Type I esophageal hiatus hernia. The superior image shows the hernia in situ where the stomach and greater omentum are still in the hernia sac. The inferior image shows the contents reduced and the abdominal esophagus being pulled into the abdominal cavity. The dotted line shows the dilated esophageal hiatus that needs to be repaired to prevent recurrence of the pathology.

Click on this link for additional information on esophageal hiatus hernia surgery.

The image below answers a question by Victoria Guy Ratcliffe, who asked via Facebook "What would it be if it feels like you've got a blockage right at the level of the heart? That's too high for a hiatal hernia, isn't it?" The image answers the question. It shows a dissection of the left side of the thorax. The anterior thoracic wall and the left lung have been removed. The heart is immediately superior and anterior to the esophageal hiatus, and the hernia sac of a Type I esophageal hiatus hernia is seen immediately posterior and in contact with the heart. Whether this means that you will "feel" the hernia, it is up for debate, as all these structures have visceral innervation. Most probably, a well-developed Type II esophageal hiatus hernia might interfere with swallowing at this level, causing the sensation she mentions. Thanks for the question, Tori.
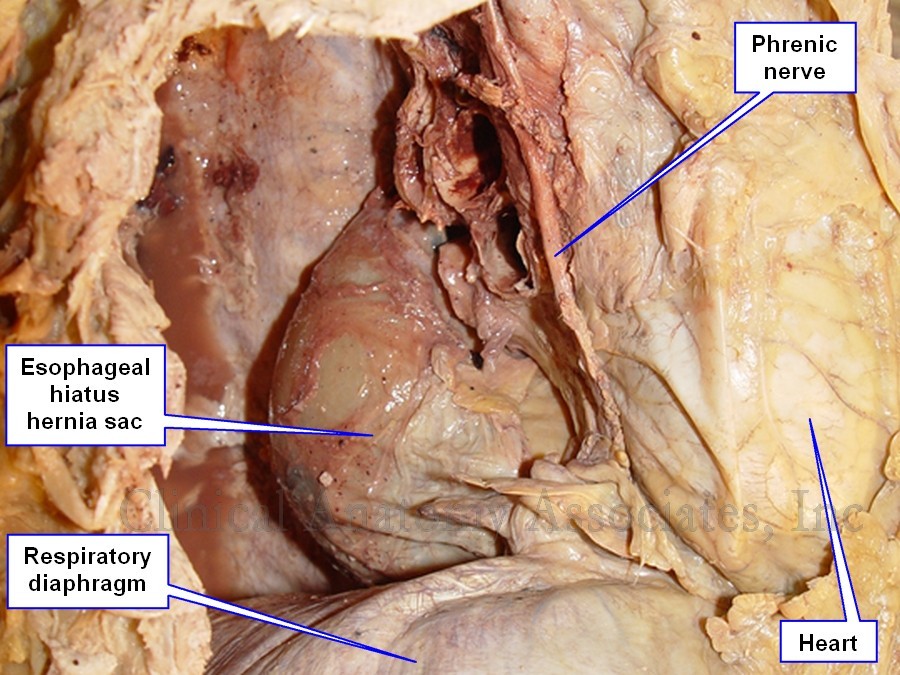
Type I esophageal hiatus hernia<em>.</em>The hernia sac can be seen posterior to the heart

For additional information:
"Approaches to the Diagnosis and Grading of Hiatal Hernia" Kahrilas et al Best Pract Res Clin Gastroenterol. 2008 ; 22(4): 601–616.