
Medical Terminology Daily (MTD) is a blog sponsored by Clinical Anatomy Associates, Inc. as a service to the medical community. We post anatomical, medical or surgical terms, their meaning and usage, as well as biographical notes on anatomists, surgeons, and researchers through the ages. Be warned that some of the images used depict human anatomical specimens.
You are welcome to submit questions and suggestions using our "Contact Us" form. The information on this blog follows the terms on our "Privacy and Security Statement" and cannot be construed as medical guidance or instructions for treatment.
We have 2167 guests online

William S. Halsted, MD
(1852 – 1922)
American anatomist, teacher, and surgeon, William Stewart Halsted was born in New York City, USA to a wealthy family of English origin. His father was involved in charitable work and Governor and trustee to a city hospital. Not a brilliant student initially, Halsted took an undergraduate in Liberal Arts in Yale, CT., after which he entered the Medical College of Physicians at the Columbia College, where he excelled.
As a second-year medical student Halsted applied and obtained a position in surgery at a local hospital. In here he learned about Lister’s antiseptic technique and became an adamant proponent of it to reduce infection. In 1877 Halsted obtained his MD. After a short time as House Physician at the New York Hospital, Halsted traveled to Europe to further his education studying for two years at the Universities of Vienna, Leipzig, and W?rzburg.
Besides being at the forefront of surgical and antiseptic techniques (introducing the use of rubber gloves in surgery), Halsted was extremely concerned with the way medical students were taught in the US. He pioneered bedside clinical round discussions with the medical students after two years of basic sciences studies. Halsted developed the idea of a patient chart; he also developed the residency program for medical students in use today.
Halsted is probably the most influential researcher and surgeon at the turn of the century. He dedicated time to the study of intestinal anastomoses and the use of silk as a suture material. His experimental work in 1887 proved that the inclusion of the submucosa layer in an anastomosis was mandatory, as well that a single layered anastomosis was enough to attain closure. Perhaps Halsted’s most important contribution was the application and use of the scientific method to surgical questions. Halsted’s principles, also known as "Halsted's Rules of Surgery", set the standards used today in surgical suturing and surgical stapling.
He also pioneered the development and surgical techniques for radical mastectomy as a treatment for breast cancer.
As a side effect of this studied in anesthesia and the use of cocaine for anesthesia, Halsted became addicted to this substance, a problem that followed him through the years. Without impairing his capacity as a researcher and a surgeon, Halsted eventually recovered. He died in Baltimore in 1922 as a complication to surgery.
Sources:
1. Dubay, A. D., & Franz, G. M. (2003). Acute Wound Healing: The Biology of Acute Wound Failure. Surg Clin NA, 83, 463-481.
2. Halsted, W. S. (1887). Circular Suture of the Intestine - An Experimental Study. Am J Med Sci, 436-461.
3. “William Stewart Halsted: his life and contributions to surgery” Osborne, P. Lancet Oncol 2007; 8: 256–65
4. “William Stewart Halsted: Surgical pioneer” Burress, P Endoc Today (2010), 8: (2) 22
5. “William Stewart Halsted (1852–1922) Neurological stamp” Haas, LF J Neurol Neurosurg Psych 2000;69:641
Original image courtesy of "Images from the History of Medicine" at www.nih.gov

"Clinical Anatomy Associates, Inc., and the contributors of "Medical Terminology Daily" wish to thank all individuals who donate their bodies and tissues for the advancement of education and research”.
Click here for more information


- Details

Thoracic rib, Posteroinferior view
The ribs form the lateral bony wall of the thorax. The ribs are paired and there are 12 pairs of ribs in the human thorax, most of them connecting the thoracic spine with the sternum. They are numbered from superior to inferior.
Ribs have different anatomical characteristics depending on their level. A typical rib has the following characteristics from posterior to anterior:
• Head: The head of each rib articulates with one or two ribs depending on their level. Typically ribs number 1,2, 10, 11, and 12 articulate with one vertebra, while the rest articulate with two vertebrae.
• Facets: These are the articular surfaces found in the head of each rib. They are covered by hyaline cartilage and form part of the costovertebral synovial joints. In the case of ribs 3 to 9, since they articulate with two vertebrae, they have two facets, each one called a demifacet, with an interarticular crest between them.
• Neck: A short, somewhat narrower portion of the rib that projects straight posterolaterally.
• Costal tubercle: A bony protuberance, usually with two components, one articular and one non-articular. The articular part of the costal tubercle presents with a facet that articulates with the transverse process of a thoracic vertebra.
• Costal angle: A sharp posterior curvature of the rib. The body when supine rests of these costal angles which deflect pressure from the thoracic spine.
• Costal body: The area of the rib anterior to the costal angle. In most ribs this oval-shaped region of the rib presents with an inferior and internal groove. This is the costal groove or costal sulcus. The corresponding level intercostal artery, vein, and nerve are found in the costal sulcus.
• Costal cartilage: All ribs have an anterior fibrocartilaginous component. Some of them attach directly to the sternum (chondrosternal joints), while some of them attach only to other costal cartilages (chondrochondral joints).
The 12 pairs of ribs are divided as follows:
• True ribs: Ribs 1-7, which attach by way of their costal cartilage directly to the sternum
• False ribs: Ribs 8-10, whose costal cartilage attach only to the cartilage of the superior rib, creating a lower border for the thoracic cage known as the costal margin.
• Free or "floating" ribs: Ribs 11 and 12. Their anterior cartilaginous end does not attach to sternum or other cartilage, so the end is free. The term "floating" although used, is a misnomer as these ribs do attach posteriorly to the thoracic spine.
There can be anatomical variations to the ribs, including the existence of extra cervical or lumbar ribs.
Sources:
1 "Tratado de Anatomia Humana" Testut et Latarjet 8 Ed. 1931 Salvat Editores, Spain
2. "Anatomy of the Human Body" Henry Gray 1918. Philadelphia: Lea & Febiger
Original image courtesy of bartleby.com. For more information: click here
- Details
The prefix [intra-] arises from the Latin [intera / interus] meaning "within" or "inside". This prefix is used in many medical terms such as:
- Intracardiac: Within or inside the heart
- Intraperitoneal: Within or inside the peritoneal cavity
- Intragastric: Within or inside the stomach
- Intramural: The term [mural] arises from the Latin [murus / muralis], meaning wall. Within a wall (or a septum)
- Intravenous: Within or inside a vein
- Intrathecal: Within or inside the thecal sac, or dural sac
- Details
Click for a larger image
The term [septum] is Latin, and means "wall", "division", or "partition". The plural form for [septum] is [septa]. Examples of use of this word are:
- Nasal septum: The osteocartilaginous partition between both sides of the nose
- Septum pellucidum: A transparent division between the lateral ventricles of the brain.
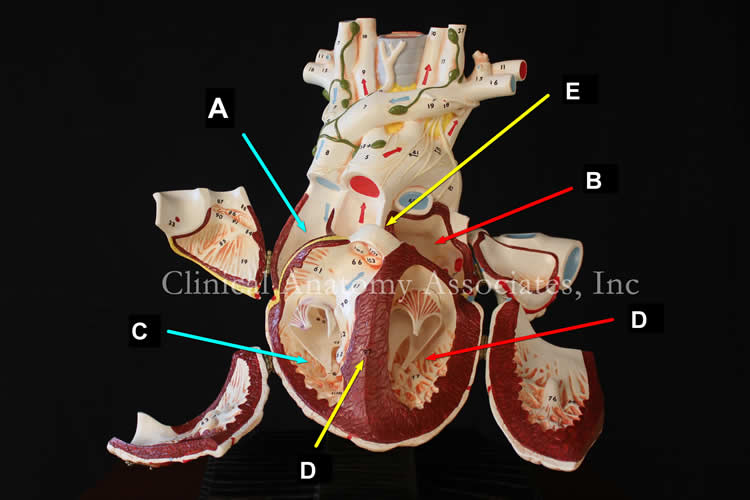
- Interatrial septum: The thin, muscular separation between the cardiac atria (see image, item "E")
- Interventricular septum: The muscular and membranous division between the ventricles of the heart (see image, item "D")
Image property of: Photographer: David M. Klein
- Details
Click for a larger image
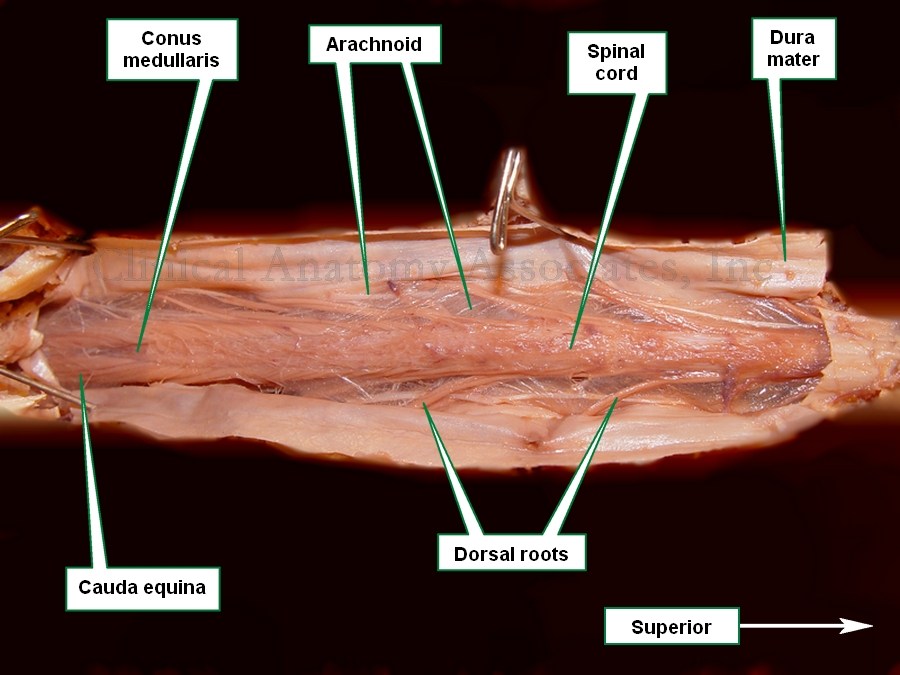
The arachnoid mater, commonly referred to only as [arachnoid], is one of the three meninges that surround, cover, and protect the spinal cord and the brain.
The first word is Greek, from [arachne] meaning "spider" and the suffix [-oid], meaning "similar to". The second word is Latin, from [mater], meaning "mother". The name arachnoid refers to the fact that in a fresh specimen the arachnoid mater looks quite like a spider's web. See the accompanying image. Click on the image for a larger version.
Embryologically, the arachnoid mater and the pia mater are considered to have a common origin, and are called the leptomeninges (thin meninges). These two membranes, internal to the dura mater, are very thin and separated by the subarachnoid space, which is filled with cerebrospinal fluid.
Image property of: Photographer: David M. Klein
- Details

Click for a larger image
The word [thorax] is Greek and means "chest", "chest plate" or an area covered by a chest plate. The root term is [-thorac-].
The thorax is the region of the trunk found between the neck superiorly and the abdomen inferiorly. It is characterized by a bony cage (thoracic cage). It is bound anteriorly by the sternum, laterally by twelve pairs of ribs and corresponding cartilages, and posteriorly by the thoracic spine, composed by twelve thoracic vertebrae.
Its superior boundary is known as the thoracic inlet or superior thoracic aperture, and it an oblique plane formed by the superior aspect of the sternum, the first rib, and the first thoracic vertebra. The inferior boundary is more difficult to describe, as there are two boundaries. The first is the inferior thoracic aperture or outlet formed by the lower end of the sternum, the cartilage of the costal margin and the most inferior ribs. The second one is the boundary between thorax and abdomen. formed by the respiratory diaphragm.
The thoracic cavity is divided into three separate regions; two laterally situated pleural regions, each containing a lung, and a centrally situated mediastinum. The mediastinum contains the heart and pericardium, the trachea and bronchi, thoracic duct, thoracic esophagus, etc.
Image property of: Photographer: David M. Klein
- Details
Click for a larger image
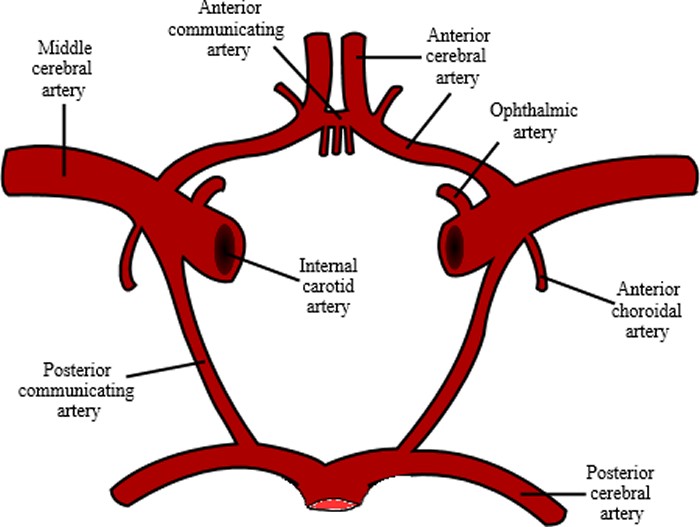
The anterior communicating artery is a single, unpaired artery found communicating both anterior cerebral arteries. The anterior communicating artery is one of the components of the arterial circle of Willis.
The anterior communicating artery is very short, usually between 2 to 3 mm in length, it is rarely absent, but it can be oblique or duplicated, or even triplicated. It is one of the sites for intracranial aneurysm. For more information on the anatomical variations of the anterior communicating artery click here.
For additional information:
"An Overview of Intracranial Aneurysms" Keedy, A Mcgill J Med. 2006 July; 9(2): 141–146Image in the public domain, modified from the . Courtesy of Wikipedia.
